Williams Cancer Institute +1 (863) 451-9755
Uterine Cancer

Uterine cancer isn't one disease. Our approach is tuned to yours.

We treat the tumor directly, through a needle, with immune drugs chosen for your type. A physician reviews your records first, free. For uterine cancer that has returned or spread, when drugs stop working.

Start Your Admissions Process How It Works

Complete a short, three-step form to begin your admissions process. One of our patient consultants will contact you to explain the process and guide you through the next steps.

What we do
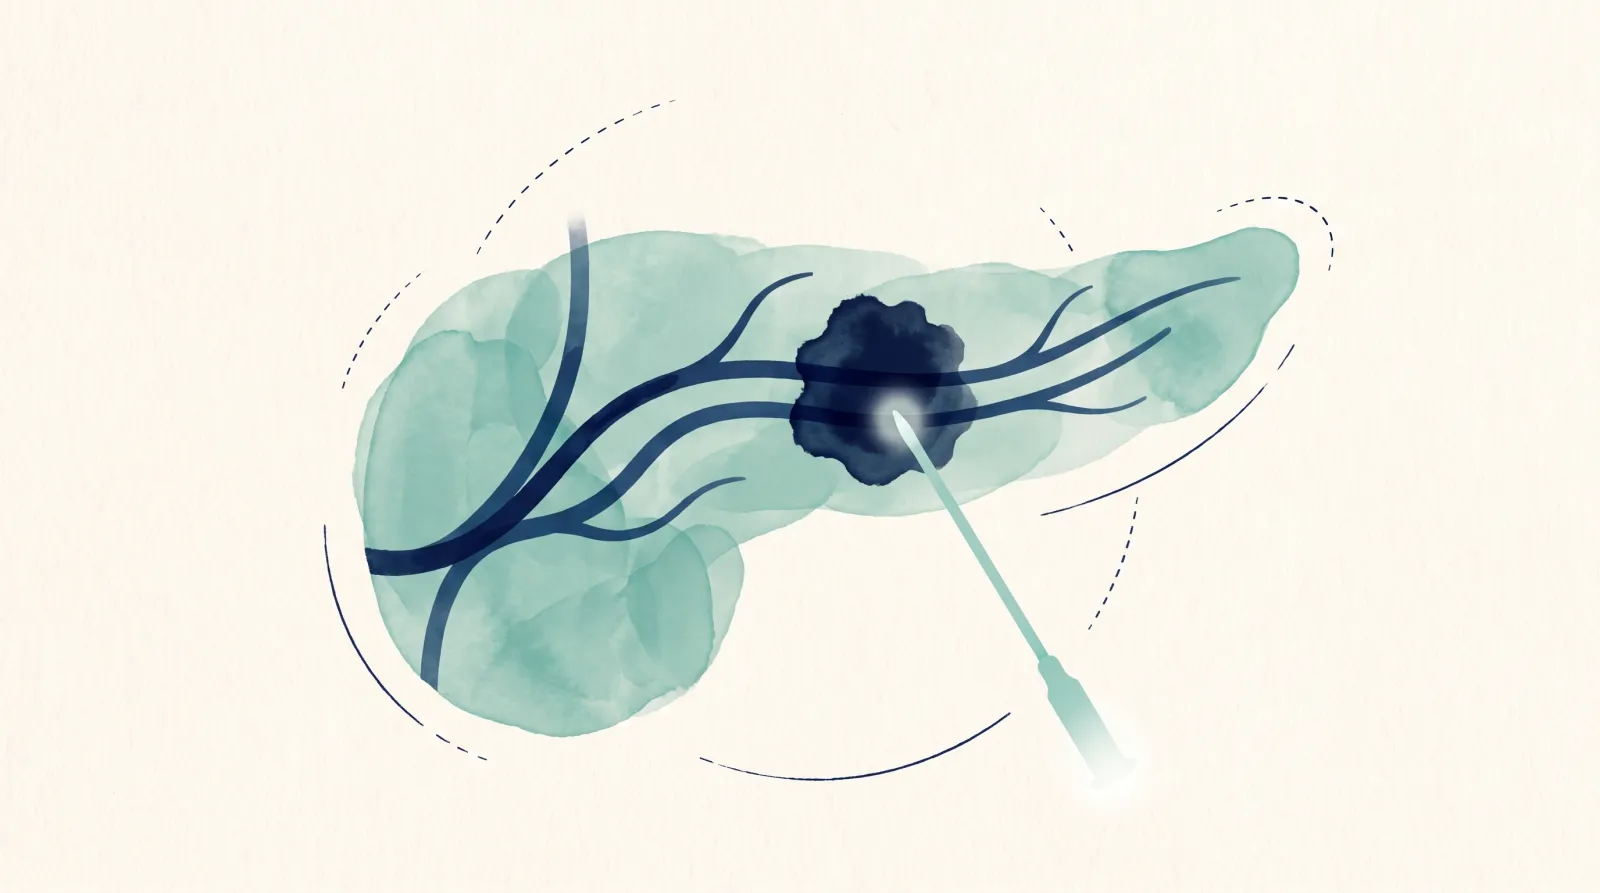
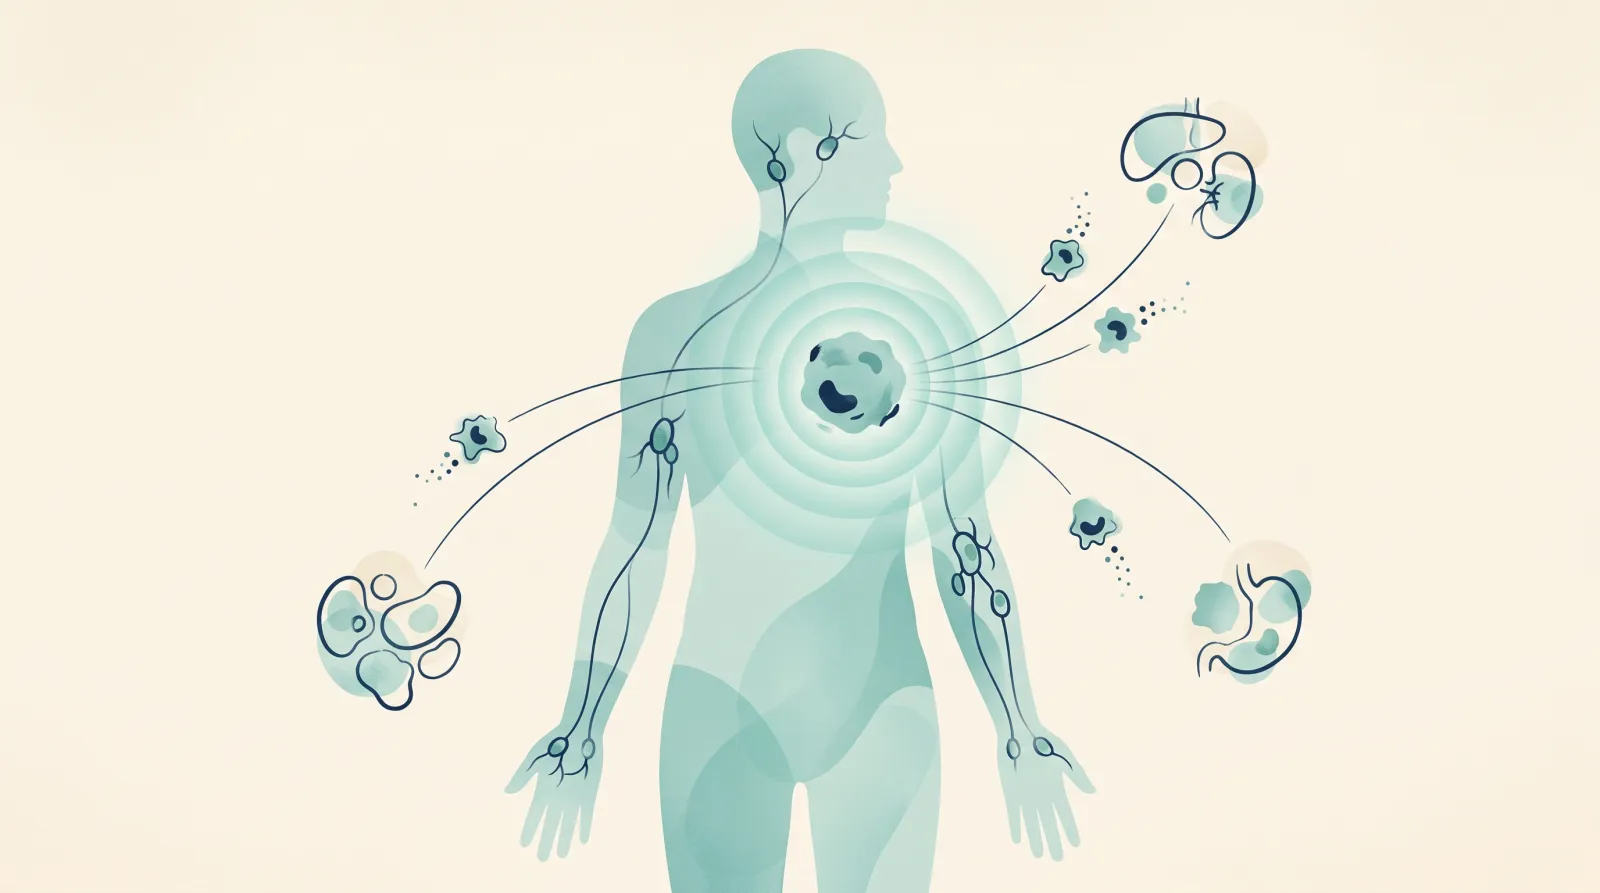
AblationVaxTreat the tumor. Teach the immune system. Treat locally, act globally.Everything we do is built on AblationVax, the approach Dr. Williams developed: the tumor is treated through a needle (ablation), and the treated tumor becomes an in-situ vaccine: a vaccine made inside your body, from your own cancer.

Two kinds of uterine cancer, two different problems

Uterine cancers come in two kinds. In one, the tumor cannot repair its DNA, and it often responds to immunotherapy; your report may call it dMMR or MSI-high. In the other, DNA repair still works and the tumor stays quiet to the immune system; your report may call it pMMR. For both, a needle breaks the tumor up, usually with electrical pulses, and injects immune drugs into it. It works alongside your current treatment, not in place of it.

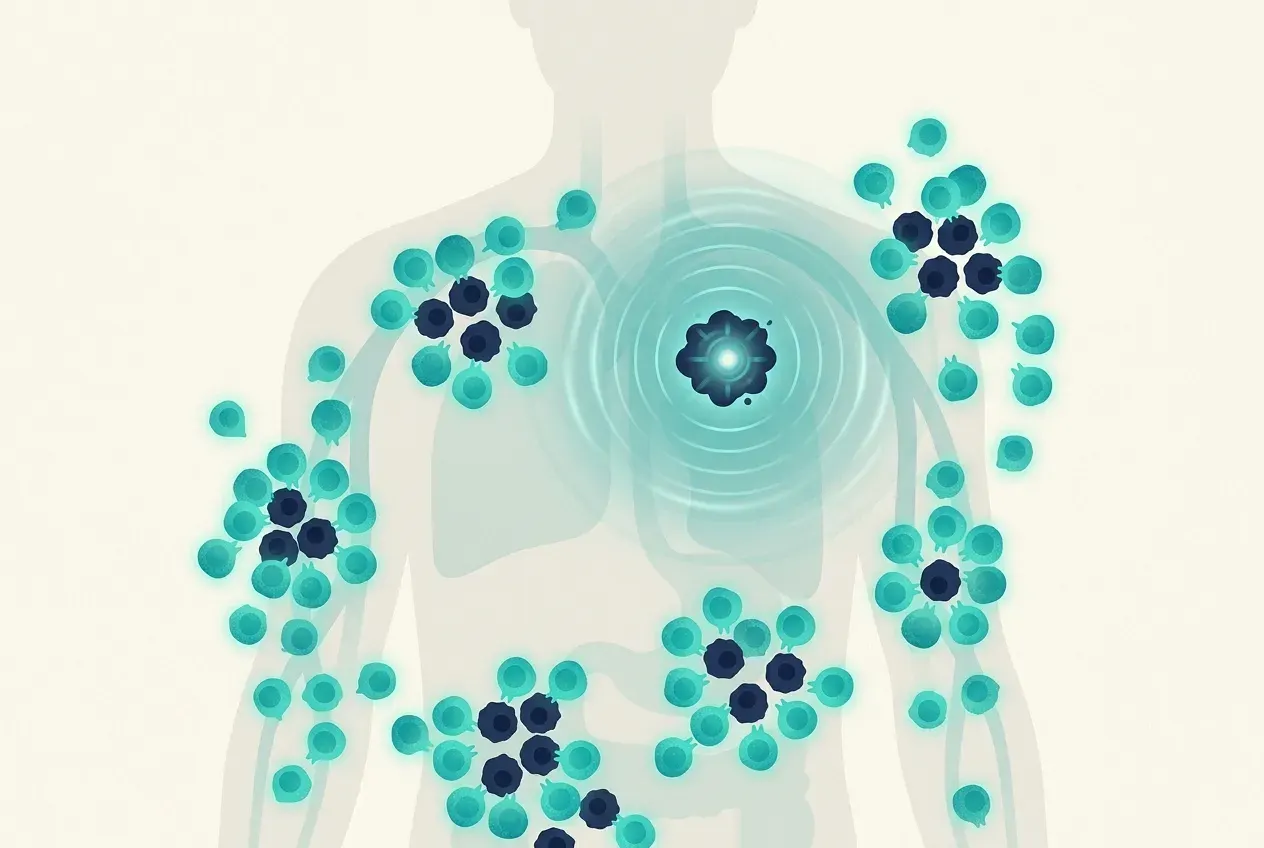
The immune drugs placed in the tumor teach the immune system to recognize this cancer, the way a vaccine does. You teach the immune system in one spot, and it goes after the same cancer in the rest of the body.

1Break it openA needle treats the tumor where it sits and breaks it open, releasing its antigens.
2Treat it in placeImmune drugs go into that exact spot, in the same session.
3Teach the whole bodyThe immune system learns the cancer at one tumor and goes after it everywhere else. Doctors call this the abscopal effect. It does not stop there: the cycle below keeps it going.
Video (1:22): Why do electricity and immunotherapy work so well together? Dr. Williams explains AblationVax.
After step 3: how AblationVax keeps working

The intratumoral immune conversion cycle

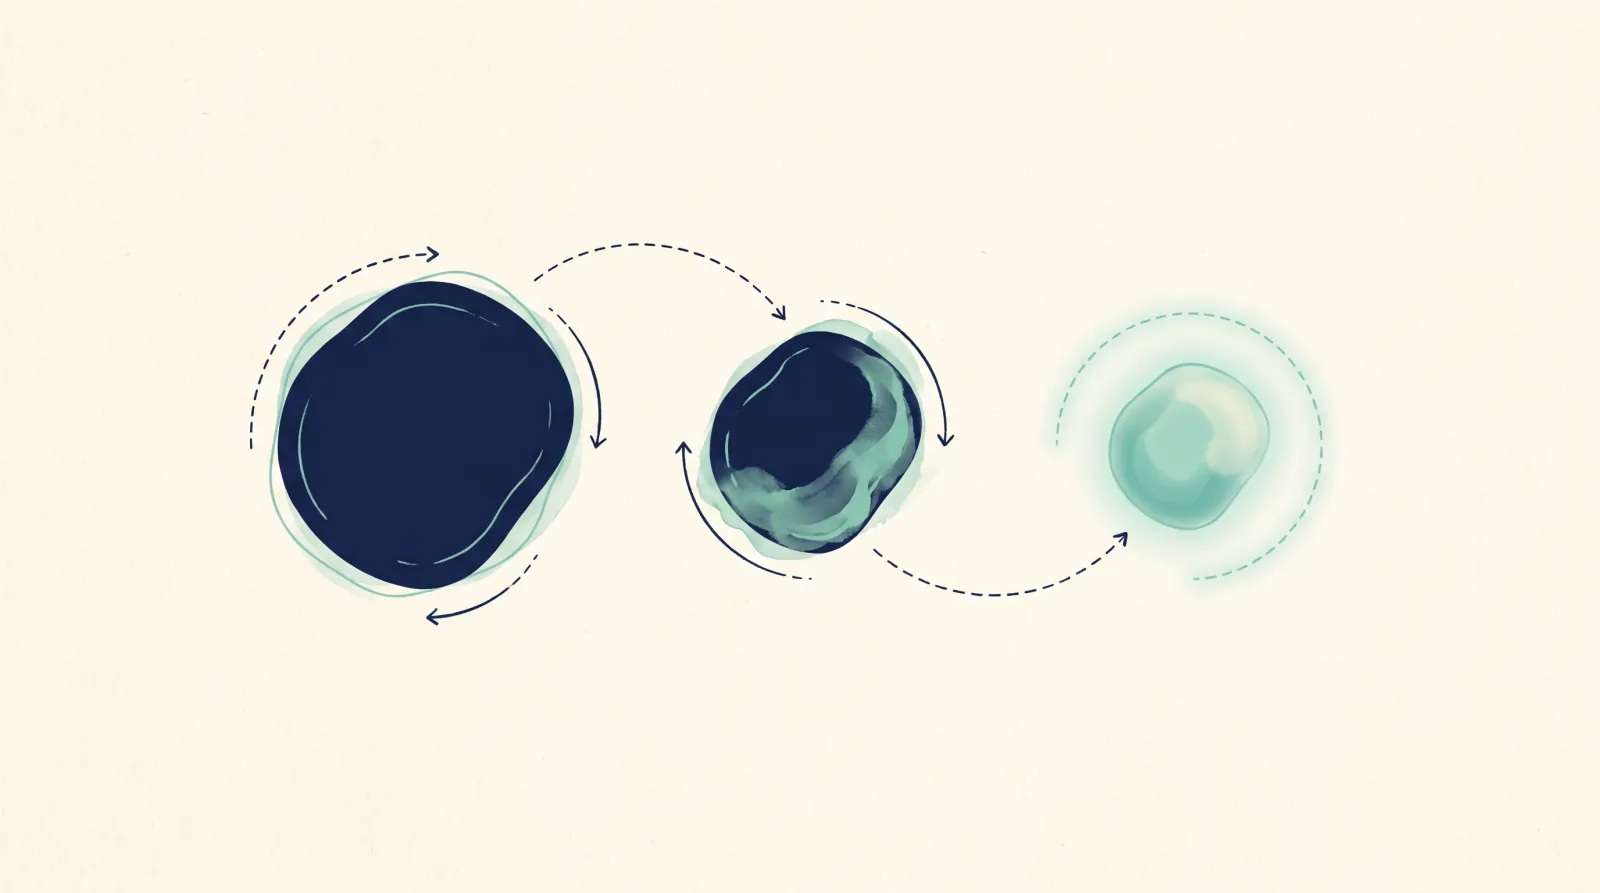
The treated tumor is the source of the vaccine, and it keeps supplying it. It is not one exposure and done. Every round of tumor cells the immune system destroys exposes new antigens, and those restart the cycle, so the response keeps spreading: broader, throughout the body, and with memory. It turns a “cold” tumor, one the immune system ignores, “hot”.

01DisruptAblation breaks the tumor open and exposes its antigens, the markers the immune system uses to recognize the cancer: not a few, all of them.
02Prime and recruitImmune drugs in that same spot call immune cells in and show them the cancer.
03Activate and co-stimulateCo-stimulation is a second go-signal. Those immune cells are switched on against the antigens the ablation just exposed.
04ReleaseThe checkpoint drugs we inject take the brakes off, so the immune system can kill tumor cells.
05DestroyImmune cells destroy tumor cells, and every cell they kill exposes new antigens.
06RepeatThe new antigens restart the cycle: re-priming, amplifying and spreading the response.

Card 06 leads back to card 02. Doctors call the widening response epitope spreading.

Most cancer vaccines: outside-inMade outside the body from a few pre-selected antigens, the same for everyone, then injected. The response is limited by the antigens someone chose.
AblationVax: inside-outMade inside your body, from every antigen in your own tumor. A vaccine made for one person: you. Not a patch: a rebuilding of the immune system from within.

Electrical pulses, not heat, next to bladder and bowel

Pelvic tumors sit against the bladder, the rectum and the tubes from the kidneys. Heat-based treatment risks them. Electrical pulses break up tumor cells without cooking the tissue around them. About an hour; most people go home the same day.

If immunotherapy stopped working, or never worked

If your tumor answered Jemperli (dostarlimab) and stopped, one idea being studied is that the immune cells have worn out; injected drugs are meant to bring in fresh ones. If it never answered, breaking it open exposes its markers.

A short procedure, not an operation

About an hour under image guidance, and most people go home the same day, about two hours later.

Reaching cancer it never touched

Once the immune system has been alerted at one tumor and kept re-primed by the cycle above, it acts on spread elsewhere in the body that was never treated, and it remembers it.

Standard care. Early disease: hysterectomy, with or without adjuvant therapy. Locally advanced disease: chemoradiation, with dostarlimab in selected cases. Recurrent or metastatic disease is treated by mismatch-repair status. Mismatch-repair-deficient tumors (dMMR, also written MSI-high: the tumor's DNA-repair system is broken, so it often responds to immunotherapy): chemotherapy with dostarlimab (Jemperli; the RUBY trial) or with pembrolizumab (NRG-GY018). Mismatch-repair-proficient tumors (pMMR: the repair system is intact and the tumor is immunologically quiet): chemotherapy with immunotherapy, or lenvatinib with pembrolizumab after platinum. HER2-positive serous carcinoma: trastuzumab-based regimens. Options narrow after progression on these lines.

Ablation alone. Thermal ablation is limited in the pelvis by the bladder, the rectum and the ureters.

This approach. Image-guided ablation of one tumor, often by non-thermal pulsed electric field (PEF) ablation because of the pelvic anatomy, followed by intratumoral immunotherapy injected into the ablation bed through the same access. The two mismatch-repair groups call for different tactics. For dMMR disease that has progressed on dostarlimab, WCI's injected immunotherapy aims at fresh effector-cell responses, on the hypothesis that the problem after checkpoint progression is T-cell exhaustion rather than a lack of antigen. For pMMR disease, which is immune-cold, the injected immunotherapy is aimed at converting the tumor locally. This combination is offered under physician review. In our clinical observations, a systemic (abscopal) effect occurs at untreated sites. Results vary.

The procedure, step by step

  1. Case review and protocol design. Pelvic MRI, PET/CT, and the molecular report (MMR/MSI status, p53, POLE, HER2, ER/PR). The intratumoral combination is tuned to the molecular subtype and to prior lines of treatment.
  2. Guidance and access. Image-guided percutaneous access to the target, by CT or ultrasound according to site: pelvic, nodal, peritoneal or distant.
  3. Ablation. Non-thermal PEF ablation where the tumor abuts bladder, rectum or ureters; cryoablation where appropriate.
  4. Intratumoral immunotherapy. Through the same access, into the ablation bed, with the combination chosen by mismatch-repair status as described above.
  5. Setting and time. Most procedures are outpatient under conscious sedation; general anesthesia or an overnight stay is rarely required. About an hour for the procedure, about two hours' recovery.
  6. Follow-up. Imaging at 6 to 8 weeks; coordination with the home gynecologic cancer team; repeat procedures as indicated. The number of treatments is decided with the patient's physician.

Agents. The injected immunotherapy is a multi-agent combination. The agents and doses are set per patient by the treating physician.

The immune conversion cycle, in clinical terms. Ablation disrupts the tumor and exposes its full antigen repertoire, not a pre-selected subset. The injected immunotherapy then remodels the tumor microenvironment, priming, recruiting and activating immune cells and releasing the brakes on them. Immune-mediated lysis exposes further antigens, which re-prime the response (epitope spreading), producing a broader, polyclonal, systemic response with memory, converting a cold tumor hot. This is WCI’s stated rationale, in Dr. Goodyear’s framing, borne out in our clinical observations.

Evidence. The published basis for intratumoral delivery is preclinical: in mice with colorectal tumors and no ablation, anti-CTLA-4 injected into a tumor reached about 14 times the day-7 level of intravenous dosing in that tumor; the untreated tumor received no more than with intravenous dosing, and half the dose reached the blood within an hour [1]. That is mouse data in colorectal cancer, not endometrial cancer; it does not test ablation and does not support a distant-site effect. WCI's own material also refers to a study of intraperitoneal checkpoint delivery in recurrent ovarian, endometrial and cervical cancer after first- and second-line treatment, on which the online candidacy check's uterine criteria are built; the route described on this page is intratumoral. No randomized trial of ablation plus intratumoral immunotherapy in endometrial cancer exists.

No uterine case with scans and a written record is on file yet. The patient accounts on this page are patients' own words, not medical records. Sources

  1. Meyblum L, et al. J Immunother Cancer 2023. PMID 37949616. DOI 10.1136/jitc-2023-007433.

Is this for you?

Where this fits, stage by stage

Your tumor's type, and what has already been tried, decide where we fit. Pick the card that sounds like your diagnosis. Whether this is right for you is decided case by case, by a physician reading your pathology and scans, so none of these lists is a verdict. If you are unsure which card is yours, send the records.

Early (stage I–II)

Cancer confined to the uterus. Standard care is a hysterectomy, sometimes with treatment afterwards, and that comes first. In selected cases we work alongside it.

Locally advanced (stage III)

Cancer has reached nearby tissue or lymph nodes. Standard care is chemotherapy with radiation, sometimes with dostarlimab. In selected cases, decided with your team, we add immune drugs inside the tumor alongside that care.

Recurrent or spread, dMMR type

Your tumor answered Jemperli and has now stopped. One explanation being studied is that the immune cells have worn out. We treat a tumor directly, injecting drugs meant to bring in fresh ones.

Recurrent or spread, pMMR type

Your tumor is quiet to the immune system and chemotherapy with immunotherapy, or Lenvima with Keytruda, has stopped working. We treat a tumor directly to try to make the immune system see it.

You may be a candidate if:

Any of these describes you:

  • Your cancer has come back or spread and is growing after Jemperli (dMMR) or after Lenvima with Keytruda (pMMR)
  • It is HER2-positive serous cancer (a type your report names) growing after Herceptin-based treatment
  • It is POLE-mutated (a gene change your report may list) and growing
  • Only a few spots are growing on your current treatment
  • You want to add immune treatment to the plan you are on
  • You are looking for options beyond your home country

It may not be suitable if:

  • There is a blockage in the pelvis with no plan to manage it
  • You have a serious infection right now, or a bleeding problem that cannot be corrected first
  • You are very unwell
  • There is fluid in the abdomen with no measurable tumor, which gives a needle nothing to aim at

Each case is individually evaluated by the Williams Cancer Institute team.

  • Early (stage I–II) — Standard care: hysterectomy, with or without adjuvant therapy. This approach is rarely first-line.
  • Locally advanced (stage III) — Standard care: chemoradiation, with dostarlimab in selected cases. Added here, under physician review: intratumoral immune priming in selected cases, alongside that care.
  • Recurrent or metastatic, dMMR — Standard care: chemotherapy with dostarlimab (RUBY) or with pembrolizumab (NRG-GY018). Added here, under physician review: direct treatment of a tumor after progression on dostarlimab, with immunotherapy injected into the tumor, aimed at fresh effector responses.
  • Recurrent or metastatic, pMMR — Standard care: chemotherapy with immunotherapy; lenvatinib with pembrolizumab. Added here, under physician review: ablation with intratumoral immunotherapy for cold disease, aiming to make the immune system respond to the tumor.

WCI's stated candidacy criteria. Recurrent or metastatic disease progressing on dostarlimab (dMMR) or on lenvatinib with pembrolizumab (pMMR) · HER2-positive uterine serous carcinoma progressing on trastuzumab-based regimens · POLE-mutant disease with progression · oligoprogressive disease on systemic therapy.

WCI's stated exclusions. Pelvic obstruction without a management plan · active severe infection · an uncorrectable bleeding disorder · very poor performance status (ECOG 3 or worse) · ascites without a measurable target (from the online candidacy check's uterine criteria). Each case is individually evaluated by the Williams Cancer Institute team.

How it works

Your Admissions Process, in Five Steps

After completing our admissions form, one of our Patient Consultants will contact you to explain the process and guide you through the next steps. Our admissions process is free of charge, including the review of your medical information and, if our medical team determines that you are a candidate, a video consultation. Treatments are generally not covered by health insurance, and WCI does not bill insurance companies.

  1. 01Free

    Initial Contact

    One of our Patient Consultants will contact you to explain the admissions process, answer your general questions, and guide you through the next steps.

  2. 02Free

    Medical Records and Imaging

    Your Patient Consultant will guide you on the required medical records and imaging studies, as well as how to submit them so our medical team can evaluate your case.

  3. 03Free

    Tumor Board Review

    Once the necessary information has been received, our medical team will review your case to determine whether you may be a candidate for our treatments. If necessary, the medical team may request additional studies or information before making a decision.

  4. 04Free

    Video Consultation

    If our medical team determines that you are a candidate, we will coordinate a complimentary Zoom consultation with one of our physicians. During this consultation, you will be able to discuss your case, address your medical questions, and learn about the treatment approach indicated for you.

  5. 05Self-pay treatment

    Treatment Plan and Next Steps

    Following your medical consultation, you will receive a personalized treatment plan that includes the corresponding costs. If you decide to proceed, the next steps will be coordinated to schedule your treatment.

    Most treatments take place in Los Cabos, Mexico; in some cases our medical team may schedule a procedure in Mexico City. Rebyota is given only at our Beverly Hills, California location.

For step 05

What to expect

Your physician confirms the details for your case.

Procedure
About an hour. Most people go home the same day.
Anesthesia or a stay
Conscious sedation is the predominant anesthesia used. It is rare that procedures require general anesthesia or an overnight stay. Your physician tells you which.
Number of treatments
Determined during the treatment plan design.
First check-up
6 to 8 weeks after the last treatment: a scan, and blood tests for your cancer type.
Your gynecologic oncologist
Kept informed throughout.
Risks

Your physician goes through the risks for your case before anything is decided.

Records to send: pelvic MRI · the most recent PET/CT · the pathology report with histology and grade · MMR/MSI, p53, POLE, HER2 and ER/PR results · a list of treatments so far, with dates. The physician confirms the list per case.

Setting. The home gynecologic cancer team is kept informed throughout. Private pay; final costs are determined during the treatment plan design.

Follow-up. First check-up 6 to 8 weeks after the last treatment: a scan; blood tests as the physician specifies. The number of treatments is decided with the patient's physician.

Dr. Jason R. Williams
Jason R. Williams, MD, DABRInterventional oncology
Dr. Williams holding the 2019 Vince Lombardi Cancer Foundation Leaders For A Cure award
Leaders For A Cure2019 · Vince Lombardi Cancer Foundation
The physician who decides every case

Dr. Jason R. Williams

MD, DABR · Director of Interventional Oncology and Immunotherapy

Dr. Jason Williams is a board-certified radiologist who has spent his career putting needles into tumors under imaging. His first patent, in 2003, covered ablation combined with immunotherapy injected into the tumor. A physician since 2000, he opened his first ablation center in 2004 and completed his residency in 2007. He also co-founded Syncromune, whose separate investigational drug SV-102 holds FDA Fast Track status. His tumor board reviews every case.

The team

Meet Our Medical Team

Tap a photo to read their background.
{{ teamSel.r }}

{{ teamSel.n }}

{{ para }}

Where treatment happens

Our Treatment Facilities in Los Cabos

Most of our treatments are performed in Los Cabos, Mexico, in a private hospital setting.

  • Imaging on site, including CT, ultrasound, MRI and digital radiology, for image-guided procedures.
  • Private patient rooms. When an overnight stay is necessary, nursing care is available on the inpatient floor.
  • Located approximately 15 minutes from Los Cabos International Airport (SJD).

Other treatment locations. In some cases our medical team may schedule a procedure in Mexico City. Rebyota is given only at our Beverly Hills, California location.

Aerial view of the Los Cabos marina at sunset
Los Cabos
Waiting lounge overlooking the Sea of Cortez
Patient lounge
Private patient room with ocean view
Private room
CT procedure suite
Procedure suite
Digital radiology room
Radiology
Patient accounts

In their own words

Accounts Williams Cancer Institute publishes, shared with each patient's permission. They span different cancers. Individual results vary and are not guaranteed.

Videos

Uterine Cancer on video

Selected Uterine Cancer videos from the Williams Cancer Institute channel. Patient stories are shared with each patient's permission. Individual results vary.
The full patient stories playlist on the Williams Cancer Institute YouTube channel.
Next step

Start Your Admissions Process

Complete our admissions form to get started. One of our Patient Consultants will contact you to explain the process and guide you through the next steps, including the medical information and imaging studies required for our medical team to evaluate your case.

info@williamscancerinstitute.com

Scan image not available in this build{{ zoomCap }}
{{ zoomCap }}